 Blogerroom
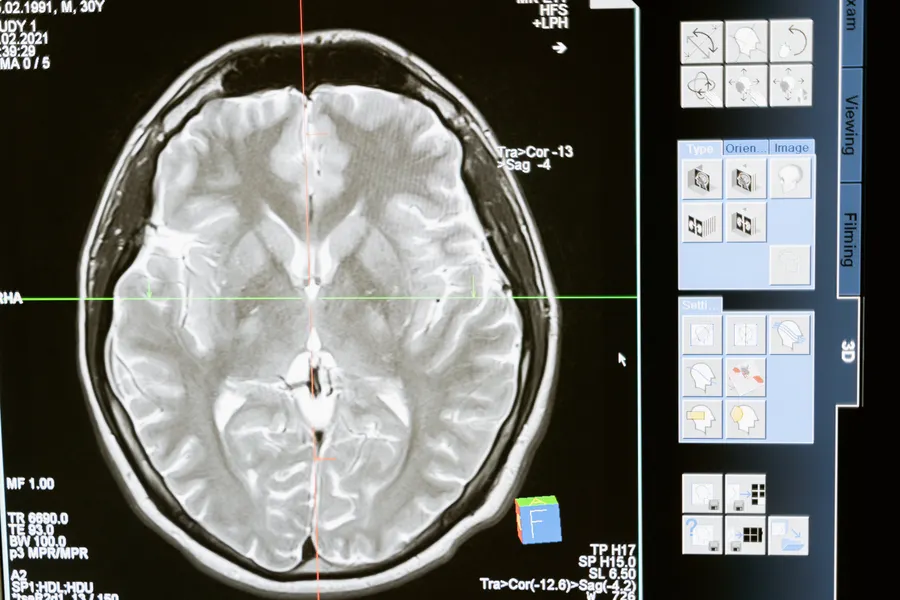
Same Depression Diagnosis, Five Different Brain Profiles
Helsinki researchers scanned 263 patients with depression using MEG and found five brain-activity profiles, some directly opposite.
Two people can walk into a clinic, describe very different struggles, and leave with the same diagnosis: major depressive disorder. A study from the University of Helsinki suggests that what lies underneath that single label may be more different than the label admits, with some patients showing brain communication that is stronger than normal and others showing communication that is weaker.
The work, published in Nature Mental Health, measured brain activity in 263 people with major depressive disorder and 75 healthy control participants. It was carried out with Aalto University and the Helsinki and Uusimaa Hospital District, and it sorted the patients into five distinct groups.
What the researchers measured
The team used magnetoencephalography, known as MEG, which records the tiny magnetic fields produced by electrical activity in the brain. Director Satu Palva of the Neuroscience Center at the University of Helsinki said the method lets researchers follow brain activity with millisecond precision. "Previously, depression phenotypes have been studied using methods with slower responses," she noted, according to Neuroscience News.
Instead of looking at one region at a time, the researchers examined functional connectivity, a measure of how strongly different brain regions work together and communicate. They combined those patterns with structural MRI and clinical symptom data, then used clustering methods to see whether patients naturally fell into groups.

Five groups, and some of them opposite
All five groups differed from healthy participants, but not in the same way. According to the University of Helsinki's summary, one group had fairly strong connectivity between brain regions and broadly severe symptoms, with depression, anxiety, rumination and reduced functional capacity pronounced. Another group had weak connectivity and milder symptoms overall.
The links to specific problems were more striking. One group with particularly strong connectivity was associated with more severe substance abuse, while another group with weak connectivity had post-traumatic stress disorder emphasized among its symptoms. "What was particularly interesting was the contrasting patterns of brain activity found under the umbrella of the same depression diagnoses," Palva said. "In some individuals, the functional connectivity between brain regions was stronger than usual, while in others it was weaker."
A possible explanation for messy earlier results
This matters because depression research has produced conflicting findings for years. Some studies reported over-connected brain networks, others reported under-connected ones. The Helsinki team argues that both may be right: if patient samples mix people from opposite profiles, the averages can blur together or cancel out.
That is a hypothesis about earlier literature, not a proven verdict on it. But it fits a pattern seen elsewhere in medicine, where an average effect hides who is actually being helped. A Long COVID drug trial recently missed its overall goal yet showed real benefit in the patients with the most severe symptoms, and a 10-year study found heart calcium scans add value only for patients at borderline risk. In each case, a single population-wide answer turned out to be the wrong question.

Why it could matter for treatment
Depression is a leading cause of disability worldwide. The World Health Organization estimates it affects roughly 332 million adults, about 5.2%, according to figures cited in the Helsinki release, and in Finland it is the most common single cause of both prolonged sickness absence and disability pensions.
Treatment today often relies on trial and error, with patients cycling through medications or therapies until something works. The researchers suggest that in the future, brain-activity patterns combined with symptoms could help clinicians identify a suitable therapy sooner and reduce that guesswork.
What the study does not show
The authors are careful about the limits. Palva said, according to Helsinki Times, "We are not yet at the point where a brain measurement could be used to select the right treatment for a patient, but the study shows one possible route towards that." The research is cross-sectional, meaning it captures patients at one point in time rather than following them, so it cannot say whether a profile predicts who will respond to which treatment.
MEG is also specialized and expensive equipment, far from a routine clinic tool. The next steps would be replicating the five profiles in other groups of patients and testing whether they map onto real differences in treatment response. Until then, the finding is best read as a sharper map of how varied depression is, and a reason to take seriously that one diagnosis may be hiding several distinct conditions.
Written by
Dr. Anand Sharma
Doctor and science communicator.

